

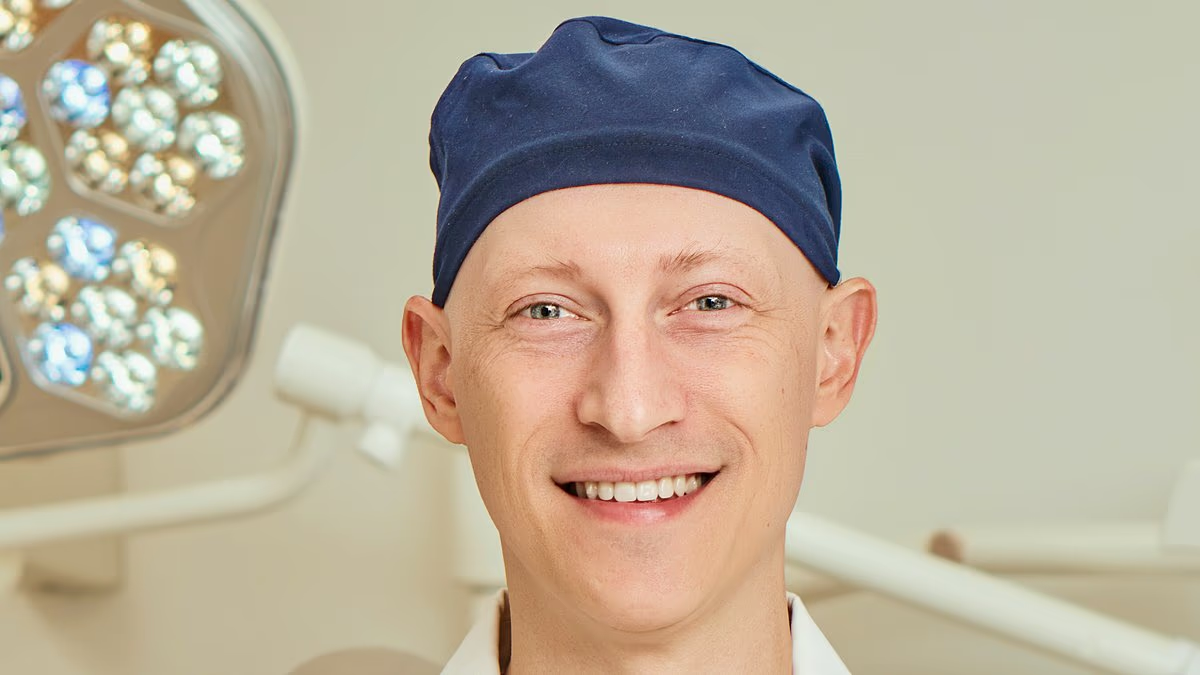
At 34, I experienced a change that reshaped both my appearance and the direction of my career.
Over the course of only a few months, I lost almost all of my hair.
Before that, hair loss had barely crossed my mind. I had always had an exceptionally thick mass of dark, curly hair—so much of it that I sometimes found it more frustrating than flattering.
Then I developed alopecia areata universalis, an autoimmune form of hair loss. The condition affected far more than my scalp: my eyebrows, eyelashes and every other patch of hair disappeared too.
At the time, I was working as a facial plastic surgeon in New York and had already started treating patients with hair loss. Moving from doctor to patient gave me a much deeper understanding of what the men sitting across from me were experiencing.
That personal experience was a major reason I chose to dedicate most of my practice to hair restoration. Since then, I have treated thousands of men dealing with hair loss.
If my work has taught me one lesson, it is that treating hair loss does not have to be as confusing or complicated as the internet often suggests.
Online, men are offered an endless range of pills, serums, injections, laser caps and experimental therapies. Yet for most men, the fundamentals of treating male hair loss are surprisingly straightforward.

Dr Gary Linkov has treated thousands of patients for hair loss at his clinic in Manhattan. He decided to focus on hair loss patients after experiencing hair loss himself
Don’t take hair loss drugs ‘just in case’
Before outlining my approach to male hair loss, there is an obvious question I should answer: if I specialise in hair restoration, why don’t I have a full head of hair?
As I mentioned, my hair loss stems from alopecia universalis, a rare autoimmune disorder in which the immune system attacks the hair follicles.
Since the condition first developed in 2008, I have tried several treatments designed to control the immune response. Most recently, I underwent immunotherapy. Some hair has gradually returned, with the clearest regrowth so far appearing in my eyebrows.
I am realistic enough to know that I am unlikely to regain the thick hair I had before.
My situation, however, is unusual. Most of the men I treat have androgenetic alopecia, commonly known as male-pattern hair loss.
The condition is largely inherited and develops when hair follicles are especially sensitive to the male hormone dihydrotestosterone, or DHT. Gradually, those follicles become smaller and begin producing hairs that are finer and shorter.
The important point is that medications are available that can slow or interrupt this process, helping to prevent further hair loss.
But does that mean you should take hair-loss medication before any signs of thinning appear, simply as a precaution?
My answer is no.
If you still have a full head of hair, have not noticed increased shedding on your pillow or in the shower, and have no receding hairline or thinning at the crown, I would not recommend starting medication.
Genetics can give you clues about what’s coming – particularly if, say, an older brother started receding at the same age.
But inheritance is much more complicated than the old idea that you simply need to look at your mother’s father to discover whether you’re going to go bald.
Until I can see evidence that something is actually changing, I’d rather wait.
These medications can cause side effects and, once you start treating male-pattern hair loss, you are generally looking at long-term treatment. There is no advantage to putting a 20-year-old on medication years before he needs it.
Often the first sign is increased shedding. Recession at the corners of the hairline is classic, and check your crown, too. I see men whose hair looks solid from the front but who are already thinning at the back.
For most men, these changes become noticeable between 25 and 35. If a guy is rapidly thinning in his late teens or early 20s, that generally means a worse prognosis.
Once you can see those changes, that’s the point to do something.
I recommend seeing somebody who regularly treats hair loss rather than simply filling out an online questionnaire and ordering medication. There is value in having somebody actually examine your hair and make sure we really are dealing with male-pattern hair loss.
From there, I divide treatment into three buckets: prevention, stimulation and augmentation.
Prevention means stopping further loss. Stimulation means encouraging weakened hair to grow thicker. Augmentation means adding hair, usually with a transplant.
If you’re serious about optimizing your hair, prevention is where I start.
The drug I always prescribe first
For most men with male-pattern hair loss, my first choice is finasteride.
It lowers levels of dihydrotestosterone, or DHT – the hormone that causes vulnerable hair follicles to progressively shrink.
In my experience, and broadly in line with the medical literature, it controls hair loss in around 90 percent of men who take it. Its main job is prevention: holding on to the hair you have.
The standard dose is 1mg a day. But this is also the drug many men are terrified to take because of what they’ve read online about sexual side effects.
They are real – but much less common than you might think. Reduced libido affects around two to three percent of men, while erectile dysfunction and changes in ejaculation can also occur.
Less commonly, patients report breast or testicular tenderness, brain fog and changes in mood.
The vast majority of men I treat take it without a problem. If somebody is particularly nervous, I’ll sometimes start more cautiously – perhaps 1mg every other day or every third day, or half a tablet.
Topical finasteride is increasingly promoted as a way to avoid side effects. It generally has less effect on DHT throughout the body, but some still enters the bloodstream and it also tends to be somewhat less effective.
If a patient is comfortable taking a tablet, I prefer oral finasteride: the dose and response are more predictable.


Linkov is pictured above before his hair loss and afterwards. He has an autoimmune condition called alopecia universalis. The main cause of hair loss is androgenic alopecia, which is linked to hormones
If that isn’t controlling the hair loss, I may move to the more powerful DHT-blocking drug dutasteride.
And for the small number of patients who simply can’t tolerate these drugs, I have prescribed five percent clascoterone, an acne cream, off-label. It works differently and is now being studied as a hair-loss treatment, with promising early results.
Why I prefer the hair loss pill to the lotion
Once we have done what we can to prevent further loss, we can think about stimulating the hair that remains. This is where minoxidil comes in.
Most people know it as a liquid or foam applied to the scalp, but in my practice I generally prefer a low-dose tablet.
Minoxidil was originally developed as a blood-pressure medication before doctors noticed that patients taking it could develop excessive hair growth.
For hair loss, I typically prescribe around 2.5mg a day. In my experience, oral minoxidil is more potent and predictable than the topical version – and, frankly, taking a pill is much easier than remembering to put something on your scalp every day.
RELATED: Ukraine Hits Russia With 1,000+ Drones as Voting Ends; 2 Dead
But not everybody needs it. If a man has some recession at the corners but otherwise really dense hair, finasteride may be enough. Minoxidil can make a much bigger difference in someone with diffuse thinning across the top of the scalp.
Because it can lower blood pressure, side effects can include light-headedness, palpitations, headaches or fluid retention. At the low doses used for hair loss, I see these in around one percent of my patients or less.
Unwanted hair growth can also occur, but at 2.5mg, when I see it, it’s almost always around the sideburns. You hear about minoxidil causing chest and back hair, but in my experience that’s more likely at doses of 5mg or higher.
Oral minoxidil is still a medication. It isn’t something I think people should simply buy online and experiment with themselves.
Don’t pin your hopes on fad treatments
There are also laser caps, injections and all sorts of sophisticated-looking devices being sold to men worried about their hair – often with a hefty price tag.
Take platelet-rich plasma, or PRP, which involves separating platelets from a sample of your blood and injecting them into the scalp.
If somebody isn’t taking anything else, they may see an improvement. But if a patient is already taking finasteride and oral minoxidil, I find it very difficult to see what additional benefit repeated PRP treatments are giving them.
I do use PRP around hair-transplant surgery because I think it can help with healing and temporary ‘shock loss.’ But I don’t generally recommend paying for injections indefinitely.
Laser caps can also stimulate the follicles and produce some improvement. But again, they’re a stimulation treatment. A laser cap isn’t going to do the same job as finasteride.

Linkov is shown above examining a patient in his clinic. He said men should see a doctor before considering starting treatment for hair loss
I have had a change of heart on microneedling – a treatment in which a stamp or roller covered with hair-fine needles is repeatedly passed over the scalp, creating thousands of tiny punctures that are intended to trigger a healing response and stimulate hair growth.
I used to think it was a useful treatment, but I now avoid it. The needles can cause scarring, which can itself affect hair growth.
I’m also concerned that microneedling is often carried out by patients themselves at home. You are relying on people to properly clean the equipment and replace the needles as often as they should – and I’m not convinced that always happens.
Reusing needles without adequately cleaning or replacing them increases the risk of infection, which can also damage the scalp and interfere with healthy hair growth.
Why a hair transplant isn’t for everyone
Then we come to the third bucket: augmentation – physically adding hair with a transplant.
This can produce a dramatic improvement in the right patient. But not everybody who is losing their hair can simply have one.
The first thing I want to know is whether their hair loss is stable.
If someone is young and losing hair rapidly, I may want them on medication for six months to a year before operating. Otherwise I could build them a new hairline only for the natural hair behind it to continue disappearing. You’re chasing a moving target.
The next question is donor hair.
A transplant doesn’t create new hair. We’re taking follicles from areas resistant to male-pattern hair loss – typically the back and sides – and moving them to where they’re needed. So there is a finite supply.
Someone with extensive loss may not have enough donor hair to recreate convincing coverage.
But you can also have too much hair for me to operate. If somebody still has 80 to 85 percent of their original density, the risk of damaging good hair can outweigh whatever improvement I could give them.
And patients need realistic expectations.
Increasingly, men come into my clinic with AI-generated images showing me exactly how they want their hair to look.
The problem is that AI can give you an impossibly dense, perfectly shaped hairline that bears very little relation to what we can achieve with a limited number of donor hairs.


Linkov says that for some men with hair loss, a hair system – attaching hair to the head that matches the hair you have lost – can be a good option. Above, James Earl, now 41, who revealed to the Daily Mail last month that he’d had a hair system fitted after topical minoxidil did not trigger hair regrowth
I would never promise to reproduce one. I’d much rather show patients photographs of real people I have treated.
And a transplant doesn’t stop male-pattern hair loss. The transplanted hairs may remain while the natural hair around them continues to thin, which is why protecting the hair you still have remains important afterwards.
Don’t dismiss a hair system
For men who aren’t suitable for a transplant – or simply don’t want surgery or medication – there is another option: a hair system.
Essentially, it’s the modern version of a toupee. They used to have a terrible reputation, and often for good reason, but the technology has come a long way and some are incredibly convincing.
For somebody with extensive hair loss or too little donor hair for surgery, I think it’s a perfectly legitimate option.
A ‘miracle’ cure might not be coming soon
I cover a lot of experimental hair-loss treatments on my YouTube channel – and I try to get excited about them because, frankly, that gets more views.
But if you ask me whether anything currently being developed is going to completely replace the treatments we already have, my answer is no.
One I am watching is clascoterone, an androgen-blocking drug already used to treat acne that is now being tested as a topical treatment for male-pattern hair loss.
I’m not convinced it will be as effective as finasteride. But it could potentially give us another option for men who simply can’t tolerate finasteride.
Another getting attention is PP405, a topical drug designed to reactivate dormant hair follicles.
Again, I’m interested. But I’m not yet convinced.
Having lost my own hair, I understand why people become desperate to try anything that promises to bring it back.
But I also know, from treating patients every day, how much misinformation there is out there.
If you notice your hair starting to change, don’t panic – but don’t ignore it either. Get advice from somebody who treats hair loss regularly, find out what type you actually have and, if treatment is appropriate, start with the options that have the strongest track record. The source of your advice matters.
There will always be a new drug, device or procedure promising to revolutionize hair loss. Some may eventually prove genuinely useful.
But don’t be so quick to jump on the bandwagon simply because something is new and exciting.
People are sometimes willing to try an experimental medication rather than something that’s been around for 40 years and is tried and true.
Sometimes it’s better to go with what we know.